
Psoriasis: Clinical Case and Comprehensive Treatment (Z. Bahridinov)
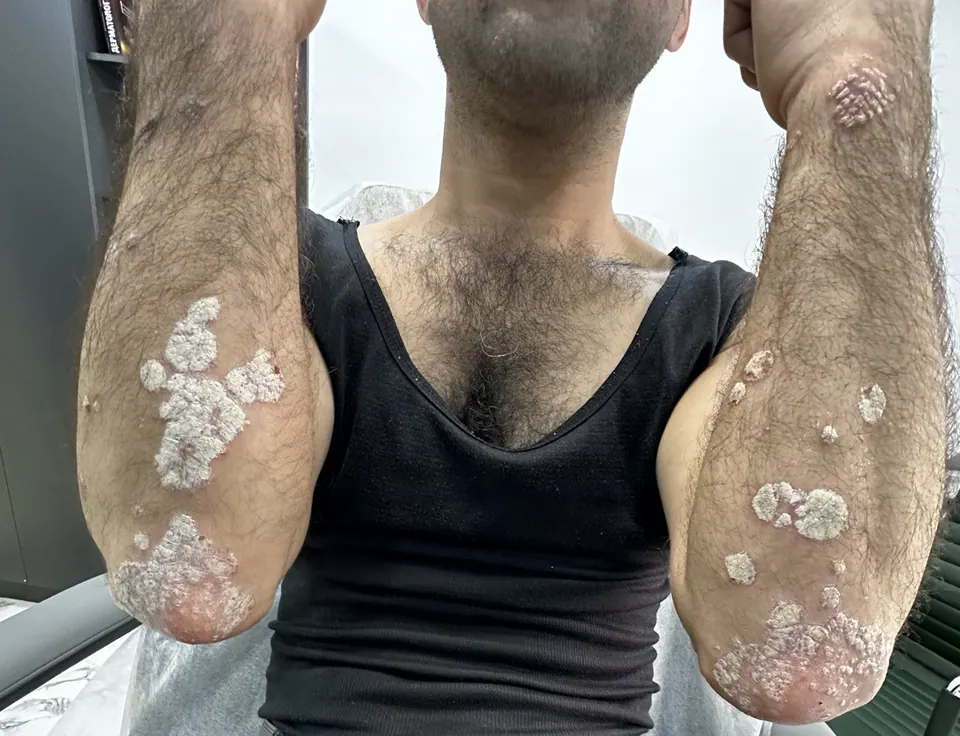
Psoriasis clinical case: UVA 308 nm, calcipotriol, 8-week outcome — Z. Bahridinov, Radeski Skin Clinic Kokand.
Key takeaways
- Plaque psoriasis often needs more than topical steroids alone
- UVA 308 nm phototherapy plus calcipotriol can be effective
- Systemic steroids carry serious rebound risk in psoriasis
- PASI may improve by ~95% in 8 weeks with a structured plan
- Protocols are individualized after workup
Clinical Case: Comprehensive Psoriasis Treatment
Author: Z. Bahridinov · Clinic: Radeski Skin Clinic, Kokand
This article describes diagnosis, an individualized protocol, and 8-week outcomes in progressive plaque psoriasis.
Why the patient came
A 34-year-old man reported intensely itchy, red, scaling plaques on the scalp, elbows, and knees. Sleep and mood were affected.
Disease duration 3 years; sharp worsening over the last 2 months (season + work stress).
Prior treatments
Topical corticosteroids elsewhere and home remedies (herbal washes, tar soap).
Steroids gave short relief with rebound after stopping. Home remedies increased dryness and itch.
At presentation
- Phase: active, progressive
- Sites: scalp crown, both elbows and knees
- Psoriatic triad positive
- Diagnosis: vulgaris plaque psoriasis, progressive stage; moderate-to-severe PASI
Workup
Examination, scraping, punch biopsy, dermoscopy, CBC (ESR↑), liver/kidney labs, CRP, rheumatoid factor (negative).
Why this protocol?
Psoriasis is systemic autoimmune skin disease with 6–7× faster cell turnover. Topicals alone are not enough.
- Narrowband UVA 308 nm phototherapy
- Calcipotriol + zinc pyrithione (non-hormonal topicals)
- No systemic steroids — rebound risk to erythrodermic/pustular forms
Treatment course
Phototherapy 3×/week, 25 sessions; morning emollients and zinc cream; evening calcipotriol; medicated scalp care as prescribed; magnesium, B vitamins, hepatoprotectors; lifestyle advice for 8 weeks.
Outcome
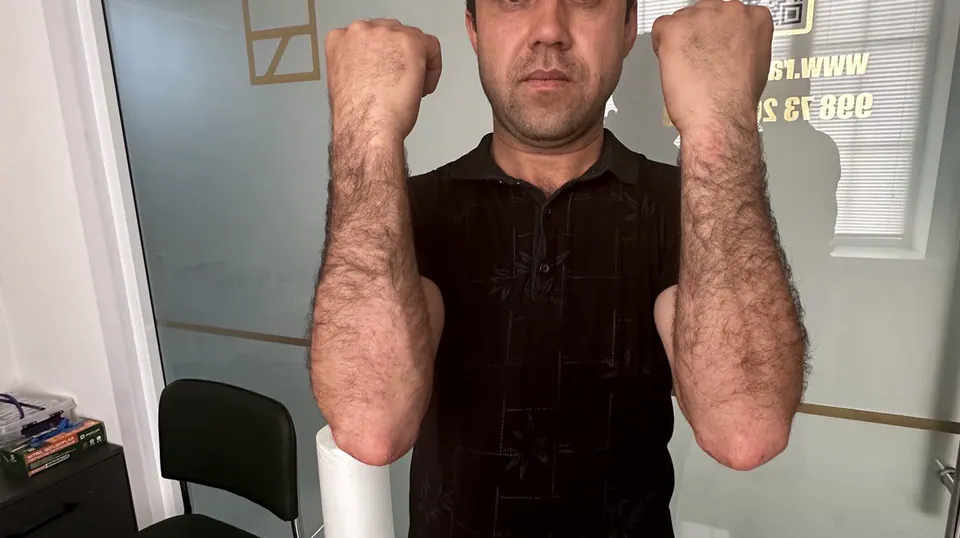
Week 2 — itch resolved; week 4 — plaques flattened; week 8 — major clearance, ~95% PASI reduction, CRP normalized.
Physician comment
Long remission is achievable with the right combined therapy. UVA 308 nm + calcipotriol reduced steroid dependence. Erythrodermic psoriasis or psoriatic arthritis may require biologics or other systemic agents.
Related services: Phototherapy, Psoriasis school, Immunobiological therapy, Prices.
When to see a doctor
- Plaques are spreading quickly
- Flares after stopping steroid creams
- Itch disrupts sleep
- Joint pain or widespread redness
Frequently asked questions
Hashtags
#Psoriasis#Clinicalcase#Phototherapy#UVA308#Calcipotriol#RadeskiSkinClinic#Kokand
Important note: This article is for general information only and does not replace a medical consultation.
Related clinic services
More helpful articles

Psoriasis: Symptoms, Diagnosis and Treatment
How psoriasis is diagnosed and treated: main signs, dermatoscopy and severity scoring, topical therapy, Daavlin narrowband UVB 311 nm, excimer laser and biologic therapy. Fergana and Kokand.
Read more
Daavlin Phototherapy for Psoriasis in Kokand | Radeski Skin Clinic
Psoriasis treatment in Kokand with Daavlin narrow-band UVB 311–312 nm: who may benefit, how the course works, advantages, and safety precautions.
Read more
Eczema: Types, Causes and Treatment — Red, Weeping and Itchy Skin
Eczema: redness, blisters, weeping and intense itching. Types, causes, how it differs from psoriasis and fungus, treatment and winter hand care. Dermatologists in Fergana and Kokand.
Read more